




Schizophrenia and IQ: What Research Shows Before and After Onset
Do people with schizophrenia have a lower IQ? On average slightly: about half a standard deviation before onset, and risk rises 3.7% per IQ point lower. But 31% of one first-episode sample kept an average or high IQ. Here is what changes before and after onset, and why speed shows the biggest gap.

Schizophrenia and IQ are linked on average, but IQ is not a test for the illness. Years before the first psychotic episode, people who later develop schizophrenia score about half a standard deviation lower on IQ tests as a group, and the risk of schizophrenia rises by about 3.7% for each IQ point lower. Yet in one sample of first-episode patients, 31% kept an average or high IQ, and the illness occurs at every level of ability. After onset the picture is more mixed: several studies find a further decline around the first episode, one finds IQ stable over three years, and processing speed shows the largest gap of any thinking skill. This guide goes through the main studies, separates the years before onset from the years after, and explains what an IQ score can and cannot say. It is general information, not medical advice.
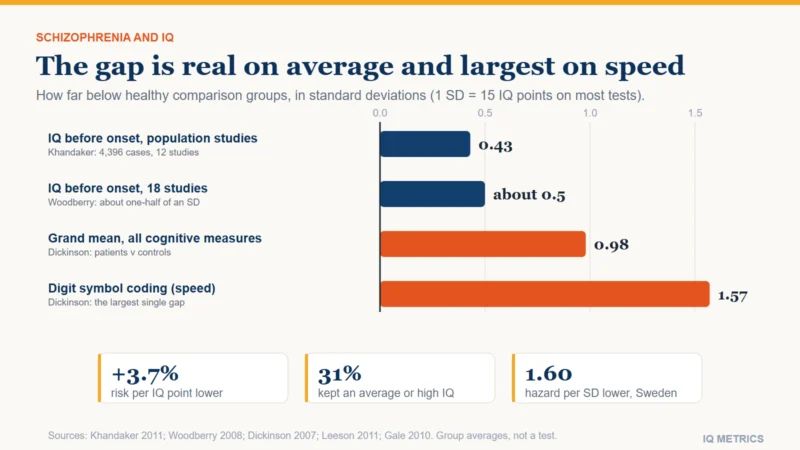
- Before onset: premorbid IQ is about half a standard deviation lower in an 18-study review, and 0.43 lower in 12 population-based studies covering 4,396 cases and over 745,000 controls.
- Dose and response: risk rises 3.7% for every IQ point lower, and among 50,087 Swedish men the risk was higher at average IQ than at high IQ, so it is spread across the whole range.
- Not everyone: of 129 people with a first episode, 25% had a stable low IQ, 31% a stable average or high IQ and 44% a deterioration of 10 points or more.
- After onset: a decline around the first episode in studies that tested before and after; later change is debated, with IQ stable over three years in one study and declines of 0.28 to 0.66 standard deviations in some skills over ten years in another.
- Biggest gap: speed. On digit symbol coding the pooled difference was g = -1.57, against a grand mean of -0.98 across cognitive measures.
- Not a diagnosis: no IQ score can diagnose or rule out schizophrenia.
This is the next guide in our series on mental health and IQ, after bipolar disorder and IQ, depression and IQ, anxiety and IQ and OCD and IQ. The wider question of whether high-IQ people have more mental illness is in high IQ and mental health. Another brain-based condition whose effect on thinking depends heavily on when it starts is covered in epilepsy and IQ.
What is schizophrenia, and how common is it?
Schizophrenia is a psychotic disorder. People may experience hallucinations, delusions or disorganized thinking and speech, often alongside “negative” symptoms such as reduced emotional expression, loss of motivation and withdrawal from others, and difficulties with attention, memory and planning. It does not mean having multiple personalities, a common mix-up. A clinician diagnoses it from the pattern of symptoms over time; no blood test, scan or IQ test can make the diagnosis. Whether intelligence relates to loneliness in the general population is a separate question, covered in are smart people lonely.
A worldwide systematic review by McGrath and colleagues found a median incidence of 15.2 new cases per 100,000 people a year, a median lifetime morbid risk of 7.2 per 1,000 people, and 1.4 men affected for every woman. Those baseline numbers matter below, because a relative risk is easier to judge against a small absolute risk.
Do people with schizophrenia have lower IQs? The evidence before onset
The most informative studies measured IQ before anyone was ill. Researchers followed people from childhood or conscription, then counted who later received a diagnosis. Two meta-analyses pool them.
| Meta-analysis | Studies and people | Finding |
|---|---|---|
| Woodberry, Giuliano and Seidman, 2008 | 18 studies | About one-half of a standard deviation below healthy comparison subjects, a medium-sized impairment |
| Khandaker and colleagues, 2011 | 12 population-based studies: 4,396 cases, over 745,000 controls | Effect size -0.43; verbal and nonverbal measures equally affected; a greater deficit went with earlier onset |
Half a standard deviation is 7 or 8 points on a scale with a standard deviation of 15, and 0.43 is about 6 points (our arithmetic). So the typical person who later develops schizophrenia scored around 92 to 94 beforehand where the population average is 100, which is within the average band; see what an IQ of 85 means for the range just below. That is a group average sitting in the middle of a very wide spread. Most people with scores in that range never develop the illness.
Both reviews also asked whether the deficit grows in the years before illness. Woodberry found that cross-sectional comparisons by age, and studies that repeated IQ tests in one sample, did not support a relative decline during the premorbid period. Khandaker’s meta-regression likewise found no evidence of a progressively increasing deficit before onset. In both, the gap seems to be present early.
How much does each IQ point change the risk?
Khandaker and colleagues found a consistent dose-response effect: the risk of schizophrenia rose by 3.7% for every point lower in premorbid IQ. The largest single cohort points the same way. Among 1,049,663 Swedish men tested on conscription and followed for 22.6 years on average, each standard deviation (15 points) lower IQ went with an age-adjusted hazard ratio of 1.60 (95% CI 1.55 to 1.65) for a hospital admission with schizophrenia (Gale and colleagues, 2010).
To see what that means in absolute terms, here is our own arithmetic, not a published estimate. If the 3.7% held at every step, 15 points lower would multiply the risk by about 1.7 (1.037 to the 15th power). Against a median lifetime risk of about 7 in 1,000, that is about 12 in 1,000; 15 points higher would bring it down to about 4 in 1,000. The real curve need not be so tidy, and the effect describes groups. Even at the low end the large majority of people never develop schizophrenia.
The same Swedish cohort shows the pattern is not specific to schizophrenia. For each standard deviation lower IQ the hazard was 1.50 for mood disorders, 1.51 for neurotic disorders and 1.75 for alcohol-related disorders, and Gale and colleagues concluded that lower intelligence is a risk factor for the whole range of mental disorders. Our reading is that IQ works as a general marker of vulnerability; compare the anxiety figures in anxiety and IQ.
Can someone with a high IQ have schizophrenia?
Yes. Among 50,087 Swedish conscripts followed for 27 years, Zammit and colleagues found that a lower IQ went with a higher risk of schizophrenia, and that risk was higher at average IQ than at high IQ, which they took to mean that the risk is spread across the whole IQ range. There is no score above which the illness stops. In the first-episode sample described below, 31% had a stable average or high IQ.
The link with creativity is a different question and rests on occupations, not IQ. A Swedish register study found healthy siblings of people with schizophrenia overrepresented in creative professions; we describe it in bipolar disorder and IQ. It says nothing about the intelligence of people with the illness themselves.
When do the differences first show?
The Dunedin study, a New Zealand birth cohort of 1,037 people assessed from age 3 to 32 with 96% retention, offers the closest look. Reichenberg and colleagues found that children who later developed schizophrenia differed in two ways between ages 7 and 13. Developmental deficits, which emerge early and stay stable, appeared on tests of verbal and visual knowledge, reasoning and conceptualization. Developmental lags, growth slower than peers, appeared on tests of processing speed, attention, visual-spatial problem solving and working memory. Neither pattern was seen in children who later developed recurrent depression.
In the authors’ summary, children who will develop adult schizophrenia enter primary school struggling with verbal reasoning and fall further behind in working memory, attention and processing speed as they get older. That is a pattern from one cohort, but it fits the Swedish and meta-analytic data in showing that the difference starts long before any symptoms.
Does IQ fall after schizophrenia starts?
Studies disagree about what happens after the first episode, so the honest answer is that some skills decline and how much is debated. Four studies cover most of the ground.
| Study | Design | Finding |
|---|---|---|
| Woodberry 2008 | Review of studies that tested the same people before and after onset | In all of them, IQ fell relative to comparison subjects with the onset of frank psychosis |
| Meier 2014 | Dunedin cohort: tests at 7 to 13, again at 38 | Declines in IQ and in processing speed, learning, executive and motor function; little decline in verbal ability or delayed memory; none in persistent depression |
| Leeson 2011 | 129 first episodes; 60 patients followed for 1 and 3 years | IQ stable after onset; no evidence of a continuing decline in the deteriorated group |
| Zanelli 2019 | 65 with schizophrenia, 41 with other psychoses, 103 controls, up to 10 years | Declines of 0.28 to 0.66 SD in IQ, verbal knowledge and memory; speed and executive deficits already present and stable |
Putting these together is not simple. Processing-speed deficits widened gradually through the teens in the Dunedin data but were already present and stable at the first episode in the ten-year study; verbal ability looks static before onset in one study and to decline over the following decade in another. Differences in sample, tests and timing probably explain some of this. In a 2013 commentary, Kahn and Keefe summarized the position: several studies find that decline in cognitive functioning precedes the onset of psychosis by almost a decade, whether it continues afterwards is still debated, and cognitive function is related to outcome and little influenced by antipsychotic treatment.
Where would your own score land?
Take the IIF-certified assessment and get your score with the scale it was measured on, the percentile it corresponds to and the confidence range around it — the three figures most online tests leave out.
Find your IQ score now! →Which thinking skills are most affected? Speed more than vocabulary
A full-scale IQ blends many skills, and schizophrenia does not affect them equally. In a meta-analysis of 37 studies with 1,961 patients and 1,444 comparison subjects, Dickinson, Ramsey and Gold found that digit symbol coding, a timed task in which you match symbols to digits, showed the largest single impairment: a weighted mean effect of g = -1.57 (95% CI -1.66 to -1.48), against a grand mean effect of -0.98. The gap on coding was significantly larger than on widely used measures of episodic memory, executive functioning and working memory, and clinical and study-design differences changed it little.
Coding is a processing-speed task; see processing speed and IQ, and for two simpler cousins the digit span test and the reaction time test. In the Dunedin study the speed gap kept widening while the verbal gap, which appeared early, stayed static. The practical lesson is that a single full-scale IQ can hide an uneven profile, which is why clinicians look at the index scores; see how to read an IQ test report and full-scale IQ vs index scores.
Preserved, deteriorated or low: three IQ trajectories
Averages hide the fact that people with schizophrenia are not one group. Leeson and colleagues compared current IQ with estimated pre-illness IQ in 129 people with a first episode of schizophrenia or schizoaffective disorder and found three subgroups.
| Group | Share | What the study found |
|---|---|---|
| Stable low IQ | 25% | IQ low before and after onset; no change over 3 years |
| Stable average or high IQ | 31% | IQ in the average or high range; fewer negative and disorganization symptoms than the other two groups |
| Deteriorated IQ | 44% | IQ fell by 10 points or more from the estimated pre-illness level |
Sixty patients and 27 controls were reassessed 1 and 3 years later. IQ stayed stable in the low group, and the apparent gains in the preserved and deteriorated groups were no greater than in healthy controls, which suggests practice effects. The low and deteriorated groups had longer first admissions, more core negative symptoms and worse occupational outcomes at 3 years. The authors concluded that IQ at the onset of psychosis, rather than pre-illness IQ, predicts a more severe illness. This is one clinical sample, and the subgroups depend on an estimate of pre-illness IQ.
Beyond IQ: choosing between now and later
Researchers also study how people weigh a smaller reward now against a larger one later, called delay discounting, the adult cousin of the task in the marshmallow test. A 2019 meta-analysis by Amlung and colleagues of 43 studies found steeper discounting, a stronger pull toward smaller, sooner rewards, in schizophrenia (Hedges g = 0.46, 12 studies), and also in bipolar disorder (0.68), borderline personality disorder (0.60) and major depression (0.37). The authors noted modest evidence of publication bias, which was statistically significant for schizophrenia, so treat the figure with some caution.
What an IQ test can and cannot say about schizophrenia
- It cannot diagnose or rule out schizophrenia. Diagnosis rests on symptoms and history.
- It describes a group gap, not a person. On our extrapolation above, the lifetime risk stays around 1 in 80 even 15 points below average, and people with high scores can be affected.
- The profile matters more than the total. Speed, memory, verbal and executive skills can differ widely within one person.
- An online IQ test is not a clinical tool. Scores depend on focus, sleep and mood, and carry a margin of error; see the margin of error explained and IQ test accuracy. Professional batteries are described in professional IQ tests.
- If you are worried about yourself or someone else, speak to a doctor or a local mental-health service. An IQ test is not the way to find out.
Quick answers
- Do people with schizophrenia have low IQs? On average slightly lower, about half a standard deviation before onset, but the range is wide: 31% of one first-episode sample kept an average or high IQ.
- What is the average IQ of someone with schizophrenia? There is no single figure. Before onset, by our arithmetic from the pooled effect sizes, roughly 92 to 94 against a population average of 100.
- Can you have schizophrenia with a high IQ? Yes. The risk is lower at higher IQ but is spread across the whole range.
- Does schizophrenia lower IQ? A gap exists before onset, several studies find a further decline around the first episode, and later change is debated.
- Which thinking skill is hit hardest? Processing speed: digit symbol coding showed the largest single gap, g = -1.57.
- Can an IQ test detect schizophrenia? No.
Sources
- Woodberry, K.A., Giuliano, A.J. and Seidman, L.J. (2008): Premorbid IQ in schizophrenia: a meta-analytic review, American Journal of Psychiatry, 165(5), 579-587.
- Khandaker, G.M., Barnett, J.H., White, I.R. and Jones, P.B. (2011): A quantitative meta-analysis of population-based studies of premorbid intelligence and schizophrenia, Schizophrenia Research, 132(2-3), 220-227.
- Zammit, S. et al. (2004): A longitudinal study of premorbid IQ score and risk of developing schizophrenia, bipolar disorder, severe depression, and other nonaffective psychoses, Archives of General Psychiatry, 61(4), 354-360.
- Gale, C.R., Batty, G.D., Tynelius, P., Deary, I.J. and Rasmussen, F. (2010): Intelligence in early adulthood and subsequent hospitalization for mental disorders, Epidemiology, 21(1), 70-77.
- Reichenberg, A. et al. (2010): Static and dynamic cognitive deficits in childhood preceding adult schizophrenia: a 30-year study, American Journal of Psychiatry, 167(2), 160-169.
- Meier, M.H. et al. (2014): Neuropsychological decline in schizophrenia from the premorbid to the postonset period, American Journal of Psychiatry, 171(1), 91-101.
- Leeson, V.C. et al. (2011): IQ trajectory, cognitive reserve, and clinical outcome following a first episode of psychosis: a 3-year longitudinal study, Schizophrenia Bulletin, 37(4), 768-777.
- Zanelli, J. et al. (2019): Cognitive change in schizophrenia and other psychoses in the decade following the first episode, American Journal of Psychiatry, 176(10), 811-819.
- Dickinson, D., Ramsey, M.E. and Gold, J.M. (2007): Overlooking the obvious: a meta-analytic comparison of digit symbol coding tasks and other cognitive measures in schizophrenia, Archives of General Psychiatry, 64(5), 532-542.
- Kahn, R.S. and Keefe, R.S. (2013): Schizophrenia is a cognitive illness: time for a change in focus, JAMA Psychiatry, 70(10), 1107-1112.
- McGrath, J., Saha, S., Chant, D. and Welham, J. (2008): Schizophrenia: a concise overview of incidence, prevalence, and mortality, Epidemiologic Reviews, 30, 67-76.
- Amlung, M. et al. (2019): Delay discounting as a transdiagnostic process in psychiatric disorders: a meta-analysis, JAMA Psychiatry, 76(11), 1176-1186.
Keep reading
All articles →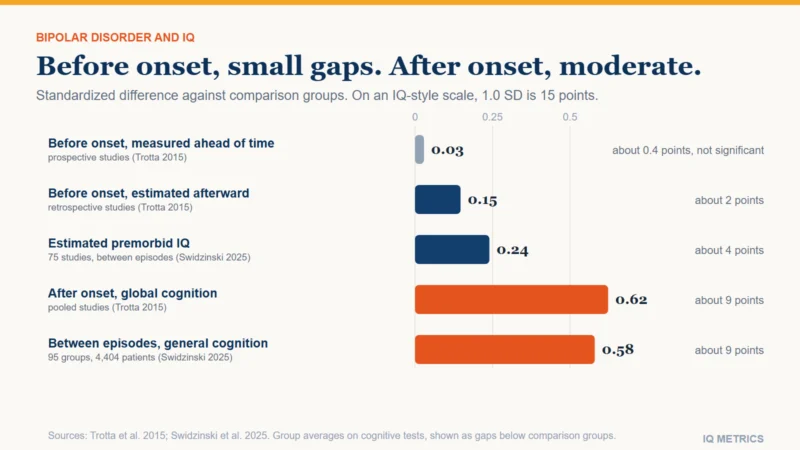 Mind & Everyday Life
Bipolar Disorder and IQ
Are bipolar people smarter? Not on average, but the evidence is more interesting than yes or no. Swedish data on a million men show a reversed-J pattern, excellent school grades carried nearly four times the risk in males, and after diagnosis cognitive scores run about 0.6 standard deviations lower.
 Mind & Everyday Life
Depression and IQ
Does depression lower IQ? It lowers performance on attention, memory, speed and planning tasks while an episode lasts, and some executive and attention differences remain after recovery. A permanent loss of intelligence is not shown, and two large cohorts suggest the arrow also runs the other way.
 Understanding IQ
Epilepsy and IQ
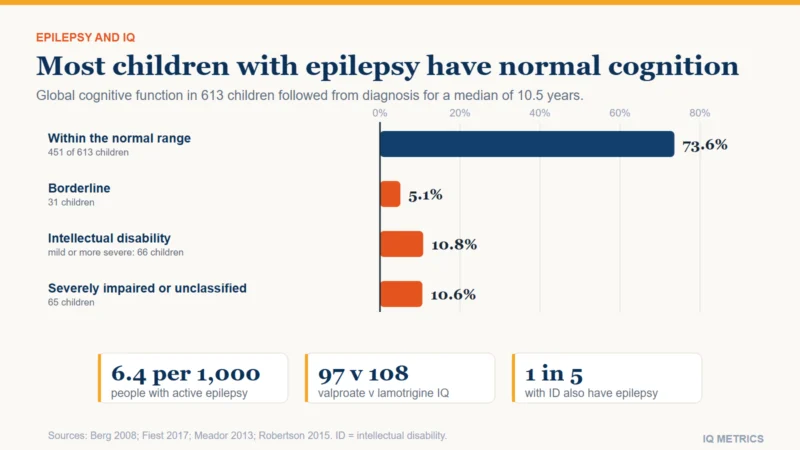
Does epilepsy lower IQ? Not in most children: in a 613-child cohort, 73.6% had normal cognition and about 1 in 4 did not. Early onset, a known cause and continuing treatment predicted lower scores, and valproate in pregnancy went with an age-6 IQ of 97. Here is what the studies show.