IQ Metrics
IIF Certified Assessment Start IQ Test
IIF Certified Assessment

Air Pollution and IQ

Research & Evidence

Air Pollution and IQ: What the Research Actually Shows

A 2024 meta-analysis pooling six studies and 4,860 children found that every rise in fine-particle air pollution came with a small, statistically significant drop in IQ scores. The same pattern shows up in aging adults living near traffic, and in a household exposure route this conversation usually leaves out entirely.


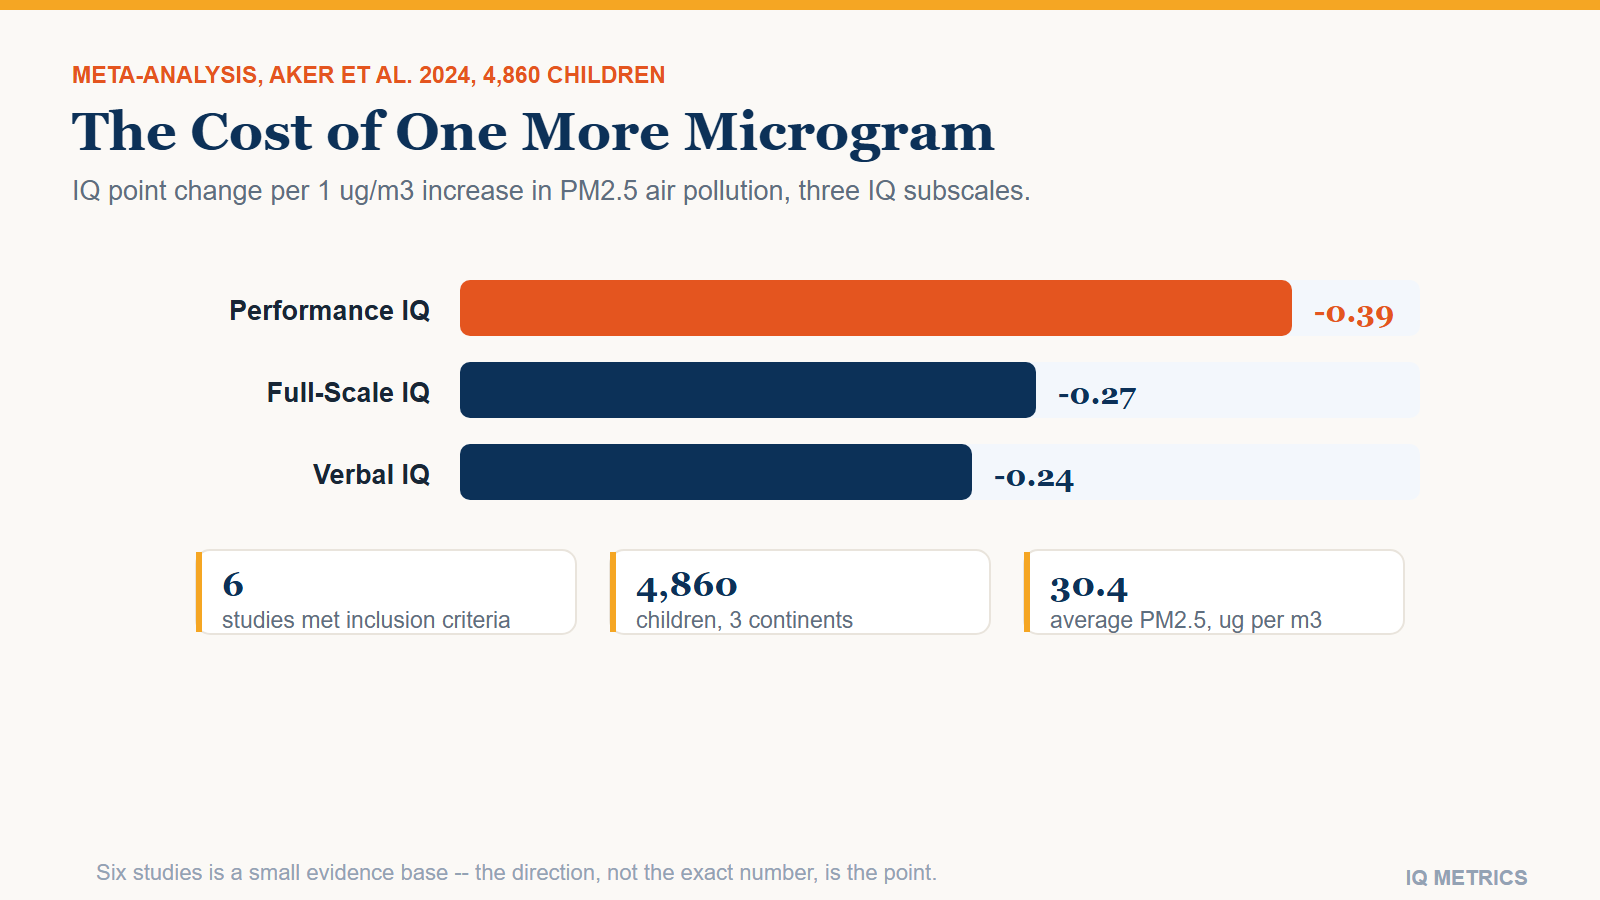
Bar chart of IQ point change per 1 microgram per cubic meter increase in PM2.5 air pollution: full-scale IQ down 0.27, performance IQ down 0.39, verbal IQ down 0.24, from a 2024 meta-analysis of 4,860 children

Yes, and the evidence is more consistent than most people expect for a topic this new. A 2024 meta-analysis pooling six studies and 4,860 children across three continents found that every increase in fine-particle air pollution was associated with a small, statistically significant drop in IQ scores. The important word there is small: this is a population-level pattern, visible when averaging across thousands of children, not a prediction about what pollution did to any one child. Six included studies is also a genuinely thin evidence base for a meta-analysis, worth saying plainly rather than treating the finding as settled.

Fine particulate matter — PM2.5, particles smaller than 2.5 micrometers, small enough to lodge deep in the lungs and, a growing body of research suggests, to reach the bloodstream — sits alongside lead as one of the more actively studied environmental exposures in child cognitive development. The two are not the same exposure and do not share a source, but they raise a similar question: what does an involuntary, population-wide exposure do to a developing brain.

What the largest analysis to date found

Published in the journal Environmental Health in 2024, the meta-analysis screened 1,107 publications against PRISMA guidelines across seven databases and found six studies that met its inclusion criteria: 4,860 children across North America, Europe and Asia, exposed to a mean PM2.5 concentration of 30.4 ± 24.4 micrograms per cubic meter, tested at an average age of 8.9. Using a random-effects model, the researchers calculated that each 1 microgram-per-cubic-meter increase in PM2.5 was associated with a 0.27-point drop in Full-Scale IQ (p<0.001), a 0.39-point drop in Performance IQ (p=0.003), and a 0.24-point drop in Verbal IQ (p=0.021). Performance IQ, the nonverbal and perceptual-reasoning subtests, showed the largest and most consistent hit of the three — the studies included do not settle why, though a similar pattern of nonverbal and processing measures being the most exposure-sensitive shows up elsewhere in the environmental-neurotoxin literature.

Bar chart of IQ point change per 1 microgram per cubic meter increase in PM2.5 air pollution: full-scale IQ down 0.27, performance IQ down 0.39, verbal IQ down 0.24, from a 2024 meta-analysis of 4,860 children

How something this small could reach a developing brain

PM2.5 is defined by size, not by a single chemical identity — it is a mix of combustion byproducts, metals and organic compounds small enough to bypass the lungs’ normal filtering and settle deep in the smallest airways. From there, the leading proposed mechanisms are a systemic inflammatory response that reaches the brain through the bloodstream, and a separate, more direct route in which the smallest particles are thought to travel along the olfactory nerve into brain tissue itself, bypassing the blood-brain barrier entirely. Neither pathway is fully settled science, and researchers are still working out how much each contributes relative to the other. What is better established is the downstream signature: postmortem and imaging studies have found markers of neuroinflammation and, in some cases, combustion-derived particles themselves inside brain tissue, which is the kind of physical evidence that turns a statistical association into a plausible causal story rather than a coincidence.

Pollution at school, not just at home

A 2015 prospective study led by researchers at Barcelona’s Centre for Research in Environmental Epidemiology followed 2,715 children across 39 schools, testing their cognitive development four separate times over 12 months. The angle was deliberately different from most exposure research: many schools sit close to busy roads, and traffic pollution peaks during the exact hours children are inside them. Children attending higher-traffic-pollution schools showed measurably slower growth in working memory over that year than children at lower-pollution schools — a finding that points at a policy-addressable variable, where schools get built and how close to traffic, rather than only a home-level exposure families have less power to change.

Your own number

Where would your own score land?

Take the IIF-certified assessment and get your score with the scale it was measured on, the percentile it corresponds to and the confidence range around it — the three figures most online tests leave out.

Find your IQ score now! →

Secure & encryptedInstant results10–20 minutes

It does not stop at childhood

A separate and growing body of cohort research links long-term air pollution exposure to faster cognitive decline and higher dementia risk in older adults: a U.S. cohort study associating midlife air pollution and road proximity with incident dementia, a Swedish longitudinal study linking traffic-related pollution to dementia incidence, France’s long-running Three-City Study finding a similar association, and a Neurology-published analysis of cognitive-decline trajectories in older adults exposed to long-term air pollution. All four are observational cohort studies, not randomized trials, and carry the obvious open question any pollution-and-health cohort does: whether people living nearer to heavy traffic differ in other ways — income, housing quality, access to care — that could independently affect cognitive aging. Researchers adjust statistically for exactly these factors, which narrows but does not eliminate the concern. What makes the overall pattern harder to dismiss is that it shows up twice, independently, in childhood development data and in adult cognitive-aging data, using different cohorts, different countries and different outcome measures.

The exposure route this conversation usually skips

Nearly all popular coverage of air pollution and cognition focuses on outdoor, traffic-related PM2.5 in wealthy cities. The far larger exposure, by concentration, happens indoors. The World Health Organization’s 2021 guidelines halved the recommended annual PM2.5 limit from 10 to 5 micrograms per cubic meter; field measurements in poorly ventilated homes using wood or coal cookstoves have documented indoor PM2.5 concentrations around 5,000 micrograms per cubic meter — roughly a thousand times that guideline. Household air pollution is linked to an estimated 70 percent of all air-pollution-attributed deaths in children under 5, and young children are disproportionately exposed because they typically stay close to their mothers during cooking, absorbing concentrations far closer to a cook’s own exposure than to anything measured outdoors nearby. Read against that number, this is substantially a global-equity question, not only a question about traffic congestion in wealthy cities, and it is the exposure route least likely to come up in a conversation about air pollution and cognition even though it is, by concentration, by far the larger one.

What narrows the exposure

None of this is a reason for panic, and it is not a reason to treat every city as equally dangerous — exposure varies enormously by location, season and even time of day, and the effect sizes above are population averages, not individual predictions. A handful of concrete, evidence-backed steps do meaningfully reduce personal exposure, for a family or a school weighing what is actually worth changing:

  • Indoor air filtration (a HEPA filter measurably lowers indoor PM2.5 in homes near heavy traffic or wildfire smoke)
  • Checking a local air quality index before strenuous outdoor exercise, particularly near arterial roads
  • Ventilation improvements or cleaner-burning cookstoves, the single highest-leverage change in the household-exposure settings described above
  • Advocating for school siting and traffic-calming decisions, since the Barcelona finding above ties exposure directly to where a building sits

The honest bottom line

The size of the effect, point for point, is small enough that no single study proves anything about any individual child or adult. What makes environmental epidemiologists take it seriously anyway is that the same direction of harm turns up repeatedly: across a meta-analysis of six independent studies, in a dedicated school-exposure cohort, and separately in adult cognitive-aging research, using different populations and different measurement methods each time. Six studies feeding one meta-analysis is not a large evidence base, and a skeptical reader is right to want more before treating the exact numbers — 0.27, 0.39, 0.24 points per microgram — as fixed. The more defensible claim is the direction and the breadth of it: several independent lines of research, run by different teams on different continents using different children and different adults, keep landing on the same conclusion, which is a higher bar to clear by accident than any one of them would be alone.

That is a different, more airborne kind of early-life exposure than this site’s companion piece on prenatal smoking, which covers a chemically distinct toxin crossing the placenta directly rather than the lungs; both sit alongside the site’s piece on chronic early-life stress as reminders that a developing brain can be shaped by exposures that have nothing to do with inherited ability.

Share this article

Know someone who keeps seeing these numbers quoted without the scale they were measured on? Send it to them.

Tagged air pollution, brain health, child iq, cognitive decline, cognitive development, dementia risk, environmental exposure, environmental health, household air pollution, intelligence research, IQ Science, neurotoxicity, particulate matter, PM2.5, traffic pollution

IQ Testing and Eugenics

Understanding IQ

Army Alpha and Beta: How IQ Testing Got Tangled Up With Eugenics

Between 1917 and 1919, the United States Army tested roughly 1.75 million recruits in the largest intelligence-testing program the world had yet seen. Within a decade, one psychologist had turned that data into a case for restricting immigration by race. Thirteen years after that, the same psychologist published a retraction few people have ever heard of.

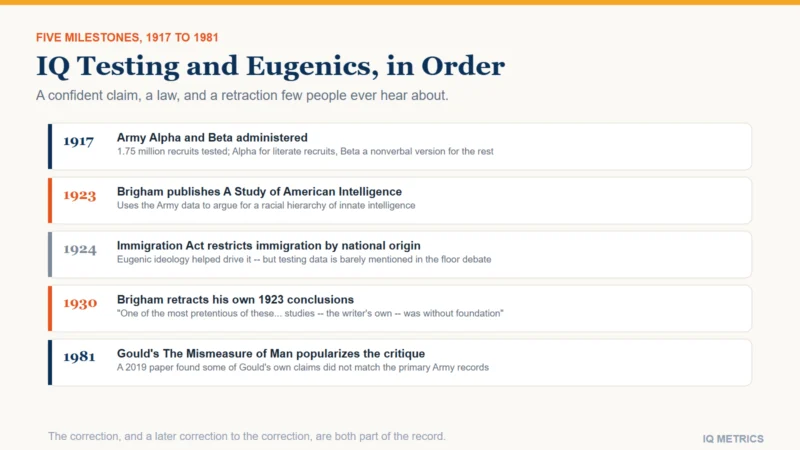
Timeline of IQ testing and eugenics: 1917 Army Alpha and Beta tests administered, 1923 Brigham publishes A Study of American Intelligence, 1924 Immigration Act restricts immigration by national origin, 1930 Brigham retracts his own conclusions, 1981 Gould publishes The Mismeasure of Man

Closely, and unhappily, for a specific stretch of the early 20th century — though less directly, and less simply, than the popular version of this story usually has it. Between 1917 and 1919, the U.S. Army tested roughly 1.75 million recruits using two new instruments, Army Alpha and Army Beta, in what was at the time the largest intelligence-testing program ever conducted. Within a few years, a young psychologist named Carl Brigham had turned that wartime data into a book arguing for a fixed racial hierarchy of innate intelligence. Within a decade after that, Brigham published a retraction of his own conclusions that almost nobody who cites his 1923 book seems to know about.

That is the responsible, checkable version of a history that gets told two ways: either as a footnote nobody looks at closely, or as a much simpler morality tale than the actual documentary record supports. Both the original claims and the standard modern correction to them turn out to have real, specific problems worth naming.

The largest intelligence-testing program in history, to that point

The Army program was directed by the psychologist Robert Yerkes, with a committee of the era’s leading testers including Henry Goddard and Lewis Terman, the psychologist who would go on to adapt the Stanford-Binet scale. Army Alpha was a written, group-administered test of analogies, arithmetic and judgment for literate, English-speaking recruits; Army Beta was a nonverbal, pictorial equivalent built for recruits who were illiterate or did not speak English. The stated purpose was practical rather than ideological on its face: classify recruits for duty assignment, screen out roughly 8,000 men judged unfit for service, and help select officer candidates, ultimately factoring into the selection of something like two-thirds of the war’s 200,000 commissioned officers.

Ellis Island, and a study smaller than its reputation

A few years earlier, the psychologist Henry Goddard had sent researchers, and later went himself, to test immigrants arriving at Ellis Island, publishing the results in 1917. The study is still cited as if it were a broad survey of immigrant intelligence; it was nothing close to that. Government physicians had already pulled aside anyone visibly disabled before Goddard’s team arrived, and the researchers then set aside anyone who looked obviously capable as well, testing only a small, deliberately ambiguous remainder. Using a looser, group-adjusted scoring standard on that unrepresentative slice, Goddard reported that more than 40 percent of the Jewish immigrants he tested scored as "feebleminded." The study’s sampling problem, not just its conclusions, is the part worth remembering: a small, pre-filtered group testing poorly on an unfamiliar, culturally loaded exam in a language many of them did not speak was reported as if it described immigrants generally.

The book that turned Army data into a racial hierarchy

In 1923, Brigham published A Study of American Intelligence, using the wartime Army Alpha and Beta results to argue for a ranked hierarchy of racial and national groups, Nordic peoples at the top, and to warn that continued immigration was driving a decline in American intelligence. The book was taken seriously in exactly the circles working to restrict immigration at the time, and it gave that political project something it wanted badly: a veneer of hard, quantitative science behind an argument that was, underneath, about who counted as fit to become American.

Timeline of IQ testing and eugenics: 1917 Army Alpha and Beta tests administered, 1923 Brigham publishes A Study of American Intelligence, 1924 Immigration Act restricts immigration by national origin, 1930 Brigham retracts his own conclusions, 1981 Gould publishes The Mismeasure of Man
Your own number

Where would your own score land?

Take the IIF-certified assessment and get your score with the scale it was measured on, the percentile it corresponds to and the confidence range around it — the three figures most online tests leave out.

Find your IQ score now! →

Secure & encryptedInstant results10–20 minutes

How much this actually shaped the Immigration Act of 1924

Here is where the popular version of this story runs ahead of the documentary record. A detailed 1983 review of the actual congressional hearings and floor debate behind the Immigration Act of 1924 found intelligence testing unmentioned in the law’s text, raised exactly once across more than 600 pages of floor debate, and criticized there without any rebuttal from supporters. None of the era’s prominent testers, not Yerkes, not Goddard, not Terman, testified before Congress or had their work entered into the official record. The reviewers’ own conclusion was that the test results were "surely not crucial" to the legislation and "most likely… immaterial" to it, a conclusion an independent 1982 review reached separately. None of that erases eugenic ideology from the story of the 1924 Act — a broader movement, and Brigham’s book specifically, were genuinely invoked in committee testimony supporting the restrictions. What the documentary record does not support is the stronger, more dramatic claim that Army intelligence-testing data was a direct or decisive cause of the law.

The retraction almost nobody remembers

In 1930, Brigham published a short paper in Psychological Review with a title that undersells what is inside it, "Intelligence Tests of Immigrant Groups." In it, he wrote that his own 1923 study — "one of the most pretentious of these comparative racial studies" — "was without foundation." His specific point was that comparing groups on a test given in English, when many test-takers had limited English fluency and limited schooling, measured language and educational access far more than it measured innate ability — exactly the kind of cultural and linguistic bias this site covers in a separate piece on test bias. It is worth being precise that the 1930 retraction focused on that methodological problem specifically; it is not a line-by-line repudiation of every claim in the 1923 book. One further, genuinely strange footnote: Brigham went on, in the years between the book and the retraction, to become the chief architect of the SAT, adapting it directly from the Army testing methodology he would later renounce for a very different purpose.

The standard modern critique, and a critique of the critique

The biologist Stephen Jay Gould’s 1981 book The Mismeasure of Man is the most widely read modern account of this history, arguing that the Army testing program was scientifically compromised, from testing conditions to culturally loaded content, and that the resulting data, filtered through Brigham, helped drive the 1924 restrictions. Two layers of scholarly pushback have followed, and they are worth keeping separate. The first, the 1983 congressional-record review described above, argues Gould overstated how directly the testing data shaped the actual legislation. The second is narrower and more recent: a 2019 paper in the Journal of Intelligence checked Gould’s specific claims about the Army Beta test itself against the original Army records and found real discrepancies — Gould described "vast numbers" of test-takers scoring zero, where the actual rate ran from under 1 to about 10 percent per subtest, and Gould cited a single unfavorable administration report while roughly a dozen more favorable ones existed in the same archive. That paper’s own conclusion is that Army Beta was, by the standards of 1917, a reasonably well-designed test. No published rebuttal of that specific finding exists yet. The pattern worth noticing is not that any one side was simply right: it is that a confident claim about what IQ data proved, made in 1923, was substantially corrected in 1930 by the person who made it, and a confident modern correction to that same history has itself since been checked, and partly corrected, against the primary record.

What actually holds up, a century later

Eugenic ideology, as a broader movement, was real, influential and genuinely tied to American immigration and sterilization policy in this period — that much is not in dispute among historians. What the specific documentary record does not support is treating IQ-testing data itself as the direct engine of that policy, rather than one piece of scientific-sounding cover recruited into an argument that was already being made on other grounds. The durable, checkable lesson is narrower than either the popular story or its detractors usually make it: a test built and interpreted carelessly, given in an unfamiliar language to people with unequal access to schooling, was read as measuring fixed, innate group differences it was never capable of measuring — and the field’s own literature, from Brigham’s 1930 paper onward, has been correcting that specific mistake in some form ever since, right up to modern work on what a heritable trait does and does not mean for group differences and to this site’s own piece on why national IQ-ranking claims do not support what people use them to argue, a modern descendant of exactly the same error. This is also not the only place on this site where a confident, well-published claim about what an IQ-adjacent measure proves did not survive later scrutiny — a very different, much more recent example plays out over years rather than decades in this site’s piece on the bilingual advantage. For the broader arc this one chapter sits inside, see this site’s general history of IQ testing.

Share this article

Know someone who keeps seeing these numbers quoted without the scale they were measured on? Send it to them.

Tagged army alpha test, army beta test, carl brigham, Cultural Bias, eugenics, henry goddard, history of iq testing, immigration act of 1924, intelligence research, iq myths, IQ Science, robert yerkes, stephen jay gould, test validity

Bilingualism and IQ

Research & Evidence

The Bilingual Advantage: What the Executive-Function Research Actually Shows

For about a decade, a well-known finding held that bilingual children and adults show sharper executive function than monolinguals. Then researchers tried to replicate it across 15 separate measures and found almost nothing. A study of conference abstracts explained part of why the early evidence looked so much stronger than what came next.

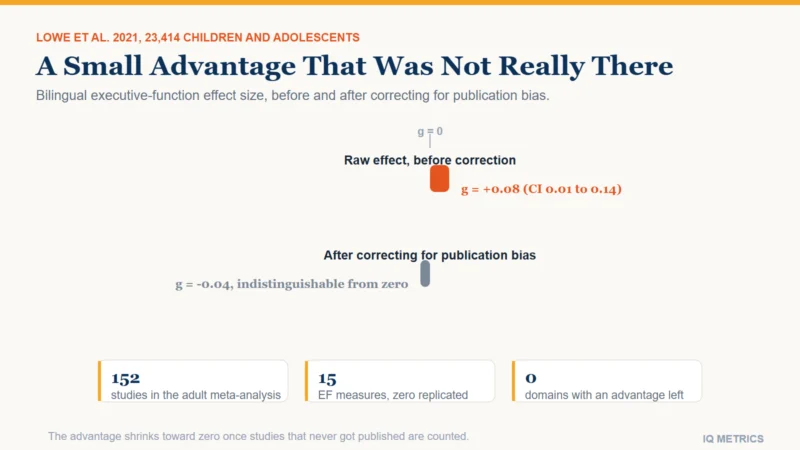
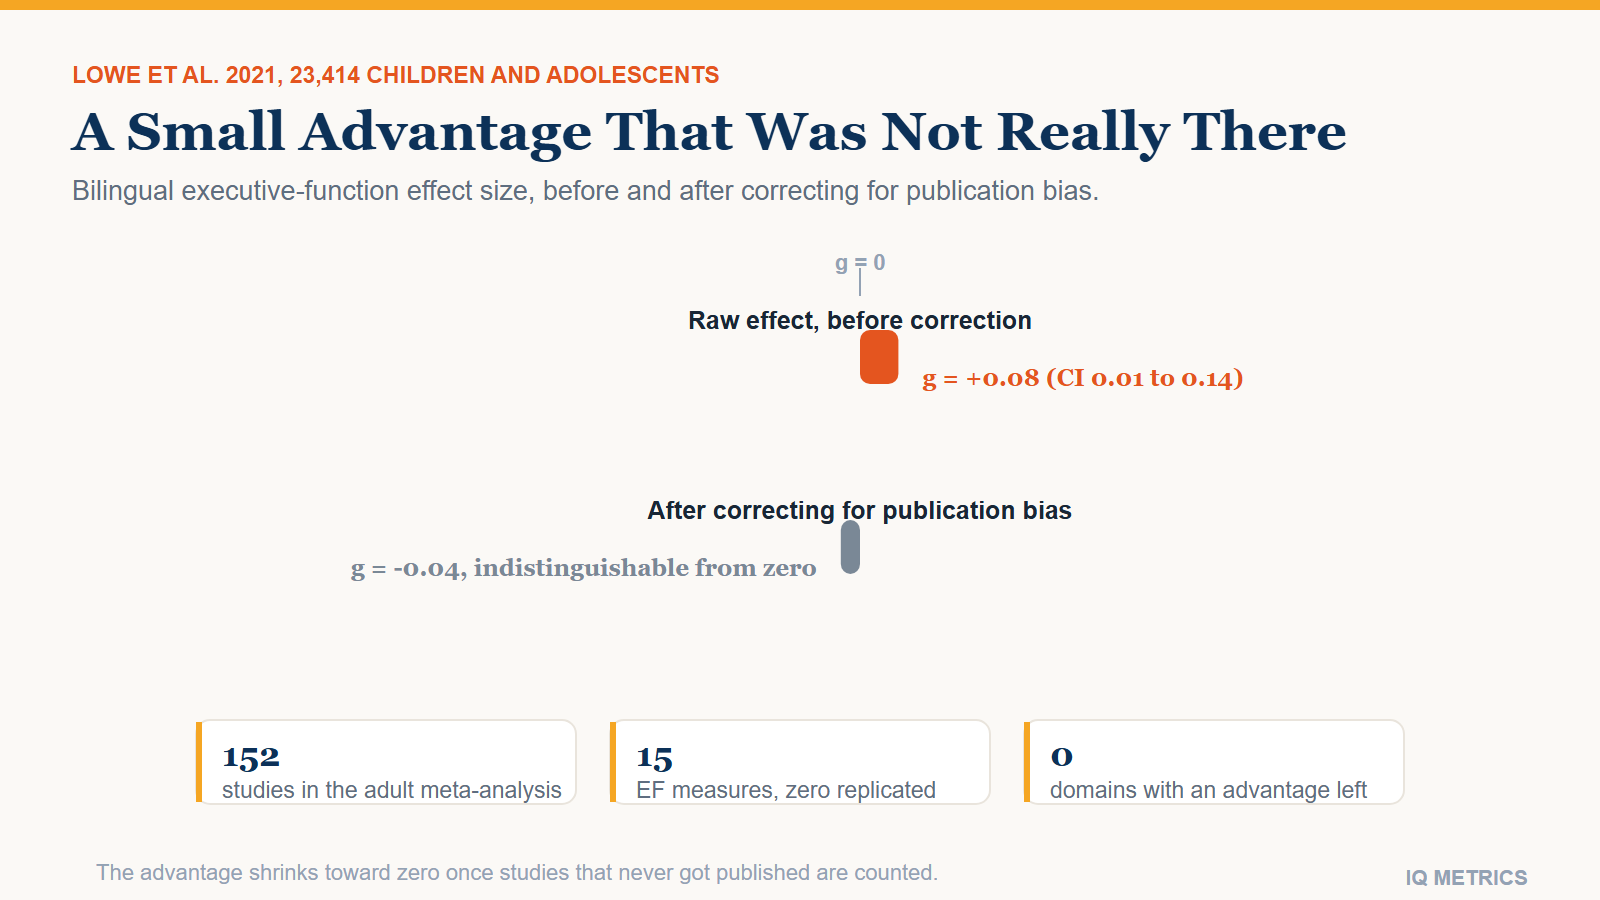
Bar chart comparing the reported bilingual executive-function advantage in children before and after correcting for publication bias: 0.08 standard deviations before correction, falling to negative 0.04, statistically indistinguishable from zero, after correction, from Lowe et al. 2021

Probably not in the way a decade of headlines suggested, and the story of how researchers found that out is a clean, well-documented case of a plausible finding failing to survive closer scrutiny. The original claim, built on real studies by a respected research group, was that juggling two languages exercises a general-purpose control system in the brain, producing an advantage on tasks that require ignoring irrelevant information. A direct replication attempt across 15 separate measures of that exact skill found essentially nothing, and a large 2021 study of more than 23,000 children — the population the original claim was actually about — reduced the effect to zero once a specific statistical bias was corrected for.

None of that means the underlying research was done badly. It means this is one of the cleaner examples in psychology of how a real, appealing early finding can look much stronger in the published literature than it turns out to be once other labs go looking for it directly.

The original finding, and why it was plausible

The foundational work came from Ellen Bialystok and colleagues, first in preschoolers using card-sorting tasks that require switching rules, then extended to middle-aged and older adults using the Simon task, a reaction-time test where a stimulus’s position conflicts with the response it requires. Bilingual participants in these studies showed a smaller performance cost from that conflict than monolinguals, and the proposed explanation was straightforward: managing two active languages and suppressing the one not currently in use functions as a kind of constant low-level exercise for a domain-general executive-control system, one that should show up on any task drawing on the same underlying skill.

The replication that did not confirm it

In 2013, researchers set out to test that prediction directly and broadly, gathering roughly 15 separate indicators of executive control across four different task types — antisaccade, Simon, flanker and task-switching paradigms — in young adults. If the domain-general theory were right, a bilingual advantage should have turned up on most of them. It did not turn up as a significant effect on any of the 15 measures, and the single interaction that did reach significance pointed toward a disadvantage for bilinguals, not an advantage. The paper’s own title stated the conclusion plainly: there was no coherent evidence for a bilingual advantage in executive processing.

Bar chart comparing the reported bilingual executive-function advantage in children before and after correcting for publication bias: 0.08 standard deviations before correction, falling to negative 0.04, statistically indistinguishable from zero, after correction, from Lowe et al. 2021

A second problem: which studies got published

A 2015 study in Psychological Science offered a specific explanation for why the published record looked so much more convincing than a direct replication did. The researchers tracked every conference abstract on bilingualism and executive control presented between 1999 and 2012, then checked which of those studies eventually appeared as full journal articles. Studies whose results fully supported a bilingual advantage were published far more often than studies with mixed or contrary results, even though the groups did not differ in sample size or statistical power — a textbook publication-bias pattern, where positive findings are simply more likely to make it into print than null ones.

What happens when you pool everything, published or not

A 2018 meta-analysis in Psychological Bulletin, deliberately built to include unpublished data alongside published studies, pooled 891 effect sizes from 152 studies of adults across six components of executive function. Before adjusting for publication bias, a very small advantage appeared in a few of those domains. After adjusting for it, the advantage disappeared in every domain tested, and a small disadvantage showed up for verbal fluency specifically, plausibly because bilinguals split their exposure to any one language across two rather than concentrating it in one.

Your own number

Where would your own score land?

Take the IIF-certified assessment and get your score with the scale it was measured on, the percentile it corresponds to and the confidence range around it — the three figures most online tests leave out.

Find your IQ score now! →

Secure & encryptedInstant results10–20 minutes

The same null result shows up in children now too

The strongest recent evidence extends the null finding to exactly the population the original claim was about. A 2021 study in Psychological Science analyzed 1,194 effect sizes from more than 23,000 children and adolescents: the raw advantage across that entire literature was 0.08 standard deviations, small but technically real. Once corrected for the same publication bias described above, that number fell to negative 0.04 — statistically indistinguishable from zero, including inside the specific "executive attention" subdomain the original theory predicted should show the clearest effect. A separate study of more than 4,500 9- and 10-year-olds in a large, nationally representative U.S. cohort reached the same conclusion using an entirely different dataset.

Where a real effect might still survive

None of this fully rules out an effect under narrower conditions than the original claim proposed. One line of newer research argues that the binary bilingual-versus-monolingual comparison used in essentially every study above may itself be part of the problem: a 2019 paper argues bilingual experience is better treated as a continuous spectrum — proficiency, age of acquisition, how immersive the environment is — than a single either-or label, so a null result on a binary comparison could still be masking a smaller, dosage-dependent effect concentrated at the far end of that spectrum. A related theory, the adaptive control hypothesis, proposes that what actually matters is not bilingual status at all but how someone uses their languages day to day — dense, moment-to-moment code-switching between two languages in the same conversation is a much heavier load on executive control than keeping two languages largely separated by context or setting, and most of the studies above did not distinguish between the two usage patterns. Neither idea has yet produced the kind of large, preregistered, bias-corrected confirmation that settled the null result above; both are the live, serious version of "there might still be something here," not a reflexive defense of the original claim.

Even the original researcher has revised the theory

In 2024, Bialystok herself published a theoretical revision in Trends in Cognitive Sciences, moving away from the original "skill transfer" account — the claim that bilingual experience directly boosts general executive function as a flat, always-on advantage — toward a narrower "adaptation" framework that predicts a benefit only under specific, high-demand conditions rather than as a general boost. That is not a minor footnote: it is the field’s founding researcher publicly updating the theory in response to exactly the pattern of evidence described above, which is roughly the scientific process working the way it is supposed to.

A different, more contested claim worth keeping separate

This site’s news desk has separately covered a different bilingualism claim, about delayed dementia symptoms in older adults, and it is worth being precise that these are not the same finding restated. Two retrospective clinic studies found Alzheimer’s symptoms appearing roughly four to five years later in bilingual patients already diagnosed with dementia. That is a different measure, symptom timing in people who already have the disease, from a healthy person’s risk of developing it at all — and when researchers restricted the analysis to the stronger prospective study designs rather than the retrospective ones, the pooled result showed no reduced risk of actually developing dementia. Retrospective clinic samples like the original two studies are also particularly prone to referral-pattern bias: which patients get diagnosed, and when, can differ systematically between bilingual and monolingual communities for reasons that have nothing to do with brain biology. If it holds up at all, this is a narrower and later-life claim than the childhood executive-function story above, not confirmation of it. A third, unrelated finding covers something else again: taking an IQ test in your second language lowers verbal-subtest scores for reasons that have nothing to do with underlying ability.

The pattern this fits

A skill developed through intensive practice failing to transfer into a broad cognitive advantage is not unique to bilingualism on this site — world-class memory athletes show the same disconnect between a trained skill and general reasoning ability, and the research on commercial brain-training programs, covered on this site’s news desk, turns up a strikingly similar gap between narrow, trained improvement and any broader intelligence gain. Skepticism toward "doing X trains your brain generally" claims is, again and again, the position the evidence keeps rewarding. It is a far gentler version of a pattern that shows up with much higher stakes in this site’s piece on IQ testing’s eugenics era: a confident, published claim about what a cognitive measure proves, later substantially walked back once other researchers looked more carefully.

Share this article

Know someone who keeps seeing these numbers quoted without the scale they were measured on? Send it to them.

Tagged bilingualism, brain training, cognitive development, cognitive reserve, executive function, general intelligence, intelligence research, iq myths, IQ Science, meta-analysis, publication bias, replication crisis, second language, Working Memory

Toxic Stress and IQ

Research & Evidence

Toxic Stress and IQ: What the Bucharest Orphanage Study Actually Found

Researchers in Romania did something that can never be done again for ethical reasons: they randomly assigned some institutionalized children to foster care and left others in the institution, then followed both groups for twenty years. The IQ gap that opened up has held at every check-in since. What has not held up as cleanly is the famous claim about exactly when the window closes.

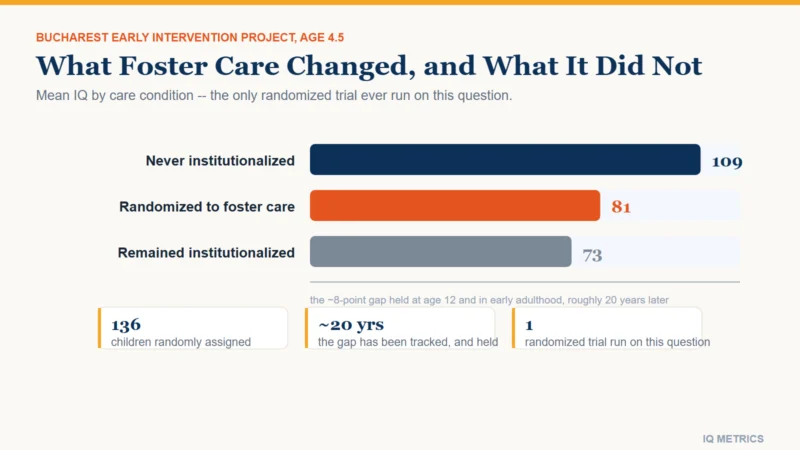
Bar chart of average IQ by care condition at age 4.5 in the Bucharest Early Intervention Project: 109 for never-institutionalized children, 81 for children randomly assigned to foster care, and 73 for children who remained in institutional care

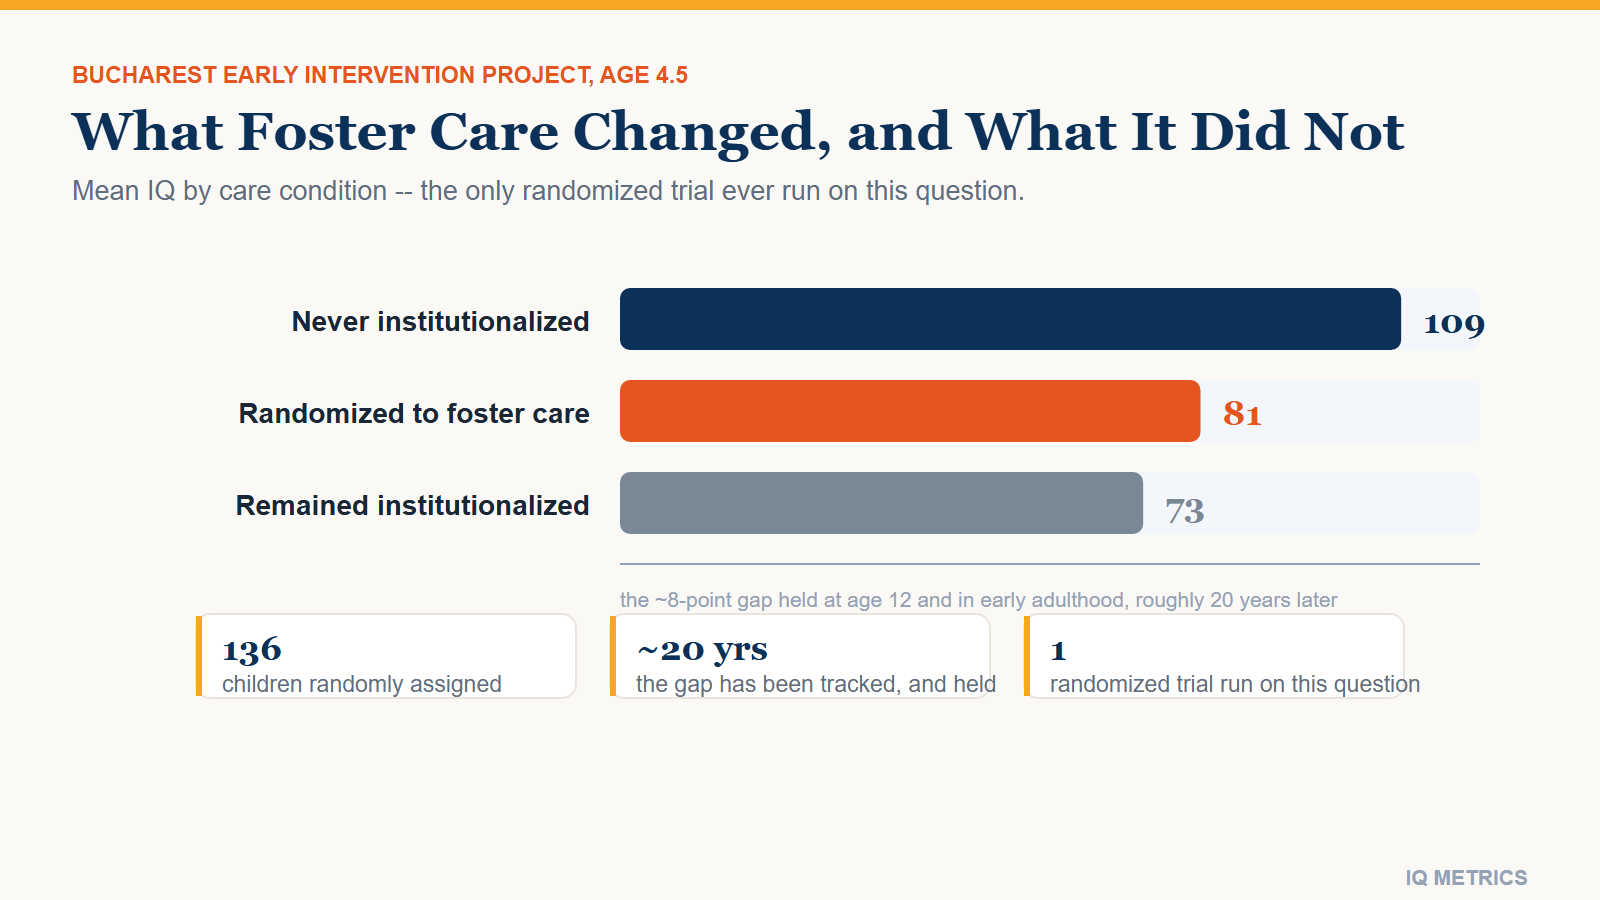
Yes, and the cleanest evidence available comes from the only randomized controlled trial ever conducted on the question — a study that could not be ethically repeated today and has followed the same children for two decades. Children living in Romanian institutions were randomly assigned either to remain in institutional care or to move into a newly created foster-care network. At the first major follow-up, the foster-care group averaged an IQ of 81, the group that remained institutionalized averaged 73, and a comparison group of children who had never been institutionalized averaged 109.

That eight-point gap between the two institutionalized groups — caused by nothing except which one got assigned to leave — is about as close to direct causal proof as developmental psychology gets. What is less solid, and worth being honest about, is the specific age-based claim that usually rides along with this study whenever it gets summarized.

The experiment nothing else in this field can match

The Bucharest Early Intervention Project enrolled 136 children, average age about 22 months, living in Romanian institutions in the early 2000s. Half were randomly assigned to continued "care as usual"; the other half were placed into foster families recruited and supported specifically for the study. A third group of Bucharest children who had never been institutionalized served as a community comparison. Because placement was randomized rather than chosen by caseworkers or families, any later difference between the foster-care and institutional groups can be attributed to the intervention itself rather than to whatever made some children more likely to be placed — the same logic, and the same rare strength, behind this site’s piece on the Perry Preschool experiment.

What the gap looked like, and how long it lasted

At 54 months, the foster-care group’s average IQ of 81 sat meaningfully above the institutional group’s 73, both well below the never-institutionalized comparison group’s 109. The gap did not fade the way some early-childhood effects do: at age 12, the same three groups scored 75.80, 68.76 and 98.61 respectively, and a 2022 follow-up in early adulthood found a foster-care group average of 73.49 against 64.65 for the group that remained institutionalized — a statistically real, roughly nine-point advantage that had held for close to twenty years. A synthesis of the full two-decade dataset, published in 2023, described the IQ effect of foster care versus institutional care as remarkably stable across the entire follow-up period.

Bar chart of average IQ by care condition at age 4.5 in the Bucharest Early Intervention Project: 109 for never-institutionalized children, 81 for children randomly assigned to foster care, and 73 for children who remained in institutional care

The "24-month window" claim, and why it deserves a hedge

The original 2007 report, and most popular coverage of it since, highlighted a striking finding: children placed into foster care before 24 months of age recovered more fully than those placed later, suggesting a sensitive window for cognitive development. That finding is real, but the later follow-ups that tested it directly did not keep reproducing it cleanly. At age 8, the cutoff that mattered had shifted to around 26 months and applied to a narrower set of measures. At age 12, the researchers explicitly tested cutoffs at 20, 22, 24 and 26 months and found no significant effect of any of them on IQ. By early adulthood, age at placement was analyzed as a continuous variable with only a marginal association, and no discrete threshold was reported at all. The honest version: a real advantage to earlier placement shows up in this dataset, but a clean, fixed "24-month cutoff" is closer to the original headline than to what the full 20 years of follow-up data actually settled on.

Your own number

Where would your own score land?

Take the IIF-certified assessment and get your score with the scale it was measured on, the percentile it corresponds to and the confidence range around it — the three figures most online tests leave out.

Find your IQ score now! →

Secure & encryptedInstant results10–20 minutes

A second, independent study that points the same way

The English and Romanian Adoptees study, a separate research group following a different cohort of children adopted out of Romanian institutions into UK families, found a 15-point IQ deficit at age 11 for children institutionalized more than six months before adoption, compared with those adopted earlier — with no further worsening for longer stays between six and 42 months. Unlike the Bucharest trial, placement into adoption here was not randomized by researchers — families made their own decisions about which children to adopt and when — so this is a natural experiment rather than a controlled one. That its findings point the same direction as a true randomized trial is exactly what makes it a useful second check, not a substitute for one. A 2017 follow-up of the same cohort into young adulthood added a genuinely useful complication: the cognitive impairment measured at ages 6 to 11 had largely remitted by early adulthood, even though psychiatric and social difficulties in the same group had not. Early deprivation, in other words, did not damage every domain equally or permanently — cognition proved more recoverable over the long run than mental health did in this particular cohort.

Why toxic stress is different from an ordinary bad day

Researchers at Harvard’s Center on the Developing Child draw a specific three-way distinction: positive stress is brief and normal, like a first day of childcare; tolerable stress is serious but time-limited and buffered by a supportive relationship; toxic stress is strong, frequent or prolonged activation of the body’s stress-response systems without that buffering adult relationship in place. The proposed biological mechanism, laid out most influentially by the neuroscientist Bruce McEwen, is that repeated activation of stress hormones produces cumulative wear on brain regions, particularly the hippocampus and prefrontal cortex, that are central to memory and reasoning. That is a plausible, well-established mechanism for how chronic stress could affect cognition, not itself a specific measured effect size — the actual evidence for the size of the effect is the Bucharest and Romanian-adoptee data above.

What the ACE study does, and does not, actually show

The Adverse Childhood Experiences study, published in 1998 and often invoked in discussions like this one, is worth being precise about: it is a retrospective survey of more than 8,000 adult patients linking childhood adversity to later adult disease and risk behavior, and it never measured IQ, cognitive test performance or academic outcomes at all. Citing it as evidence that toxic stress lowers IQ specifically overstates what the study actually did. A separate, later body of work has since made that link directly: a 2024 meta-analysis pooling 32 studies and nearly 27,000 people found a real, small-to-medium association between a higher adversity score and worse cognitive control in adulthood. That is a genuine cognition finding — it is simply a different, more recent literature than the original 1998 study, which never tested cognition at all. But even one of the ACE study’s own original co-authors has since published a caution against using the ACE score for individual-level clinical prediction, and a 2021 analysis found its accuracy at predicting any single person’s outcome to be poor, even though the population-level pattern is real. Population-level evidence and individual-level prediction are different claims, and this literature is a clean example of why that distinction matters.

What this means, and does not mean

None of this says a difficult early environment determines a fixed outcome. It says something narrower and better supported: prolonged, unbuffered early adversity is one of the few environmental factors with genuine experimental, not just correlational, evidence behind its effect on cognitive development, alongside the kind of factors already covered on this site in the piece on socioeconomic status and IQ, lead exposure and IQ, and a very different prenatal exposure covered in this site’s companion piece on fetal alcohol spectrum disorder. The size of the effect is real but moderate, it responds to intervention, as the foster-care comparison shows directly, and — per the Romanian adoptee follow-up above — even the cognitive piece of it is not necessarily permanent. The single clearest, most actionable finding across all of this research is also the simplest one: the single largest protective factor identified in both the Bucharest and Romanian cohorts was the presence of one stable, responsive caregiving relationship, which is precisely the buffer the Harvard framework above names as the difference between tolerable stress and toxic stress in the first place.

Share this article

Know someone who keeps seeing these numbers quoted without the scale they were measured on? Send it to them.

Tagged adverse childhood experiences, child iq, cognitive development, early childhood development, early intervention, foster care, institutionalization, intelligence research, IQ Science, longitudinal study, poverty and iq, randomized controlled trial, Socioeconomic Status, toxic stress

Fetal Alcohol Spectrum Disorder and IQ

Research & Evidence

Fetal Alcohol Spectrum Disorder and IQ: The Profile a Score Hides

A clinical study of 473 people diagnosed with fetal alcohol syndrome or its milder forms found that only 16 percent had an IQ in the intellectually disabled range. That statistic is not the reassurance it sounds like — it is the reason the condition is so often missed. Here is what a normal-looking score can still be hiding.

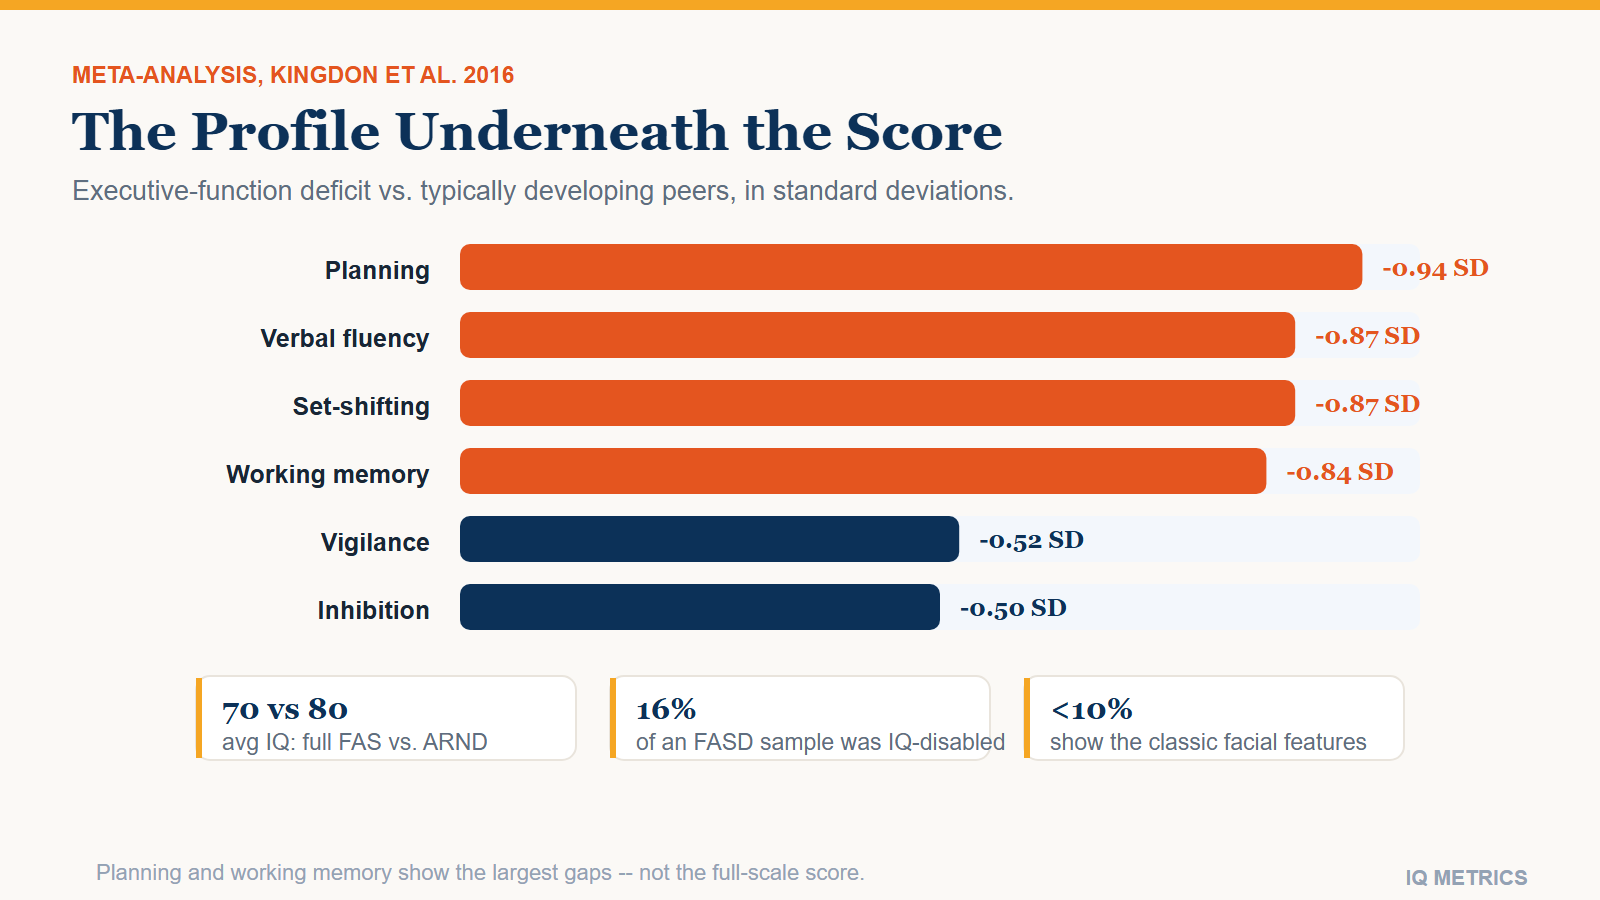
Bar chart of executive-function deficits in fetal alcohol spectrum disorder versus typically developing peers, in standard deviation units: planning 0.94, fluency 0.87, set-shifting 0.87, working memory 0.84, vigilance 0.52, inhibition 0.50 below average, from Kingdon et al. 2016

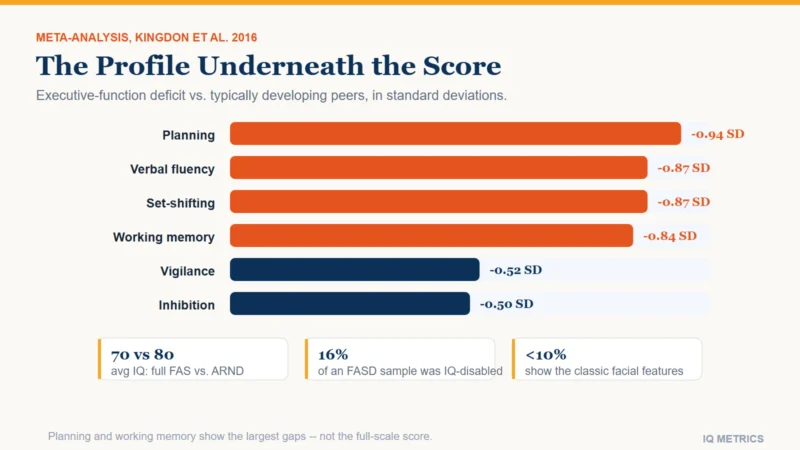
Less often than you would guess, and that gap between expectation and reality is exactly why the condition is so frequently missed. A clinic-referred study of 473 people diagnosed with fetal alcohol syndrome or a milder related condition found that only 16 percent scored in the intellectually disabled range on an IQ test. Most had an average, low-average or even above-average full-scale score — while showing a specific, measurable pattern of difficulty in a handful of other cognitive skills the score never touches.

That combination, an unremarkable composite number sitting on top of a real and specific deficit, is not a loophole in the diagnosis. It is close to the central clinical problem with fetal alcohol spectrum disorder (FASD), and it is the reason researchers have spent two decades pushing clinicians away from IQ alone and toward a specific cognitive profile instead.

What prenatal alcohol exposure does, and why there is no established safe amount

Alcohol crosses the placenta freely and can interfere with neuronal migration and brain development at multiple stages of pregnancy, with the developing brain vulnerable throughout, not only in a single early window. The CDC states plainly that "there is no known safe amount of alcohol use during pregnancy" and "no safe time during pregnancy to drink alcohol," a position the American College of Obstetricians and Gynecologists and the U.S. Surgeon General have separately reached as well. It is worth being precise about what that guidance actually claims: it is a statement that no safe threshold has been established, not a claim that every exposure at every level produces measurable harm. Heavy and frequent drinking in pregnancy is well documented to carry real, dose-related risk; the effects of very light or one-time exposure are far less firmly established either way, and treating the two claims as identical overstates what the evidence supports in either direction.

Why FASD is an umbrella, not one diagnosis

An Institute of Medicine panel in 1996 set out four categories under the FASD umbrella: fetal alcohol syndrome (FAS, the most severe, defined by a specific triad of growth deficiency, facial features and central nervous system dysfunction), partial FAS, alcohol-related neurodevelopmental disorder (ARND), and alcohol-related birth defects. The DSM-5 added a research category in 2013, neurobehavioral disorder associated with prenatal alcohol exposure, that drops the facial-feature requirement entirely and defines the condition by function instead. Worth saying plainly rather than glossing over: there is still no single international diagnostic standard. Several systems, the original IOM categories, a 2016 Canadian guideline built around impairment across specific neurodevelopmental domains, and a separately developed 4-Digit Diagnostic Code used in Washington State, currently coexist, and a 2025 systematic comparison found only fair-to-moderate agreement between them. That lack of consensus is itself a clue to what makes this condition hard to pin down.

Fewer than 1 in 10 people with an FASD diagnosis show the facial features most people associate with it. The rest, the large majority, look physically typical, which is one reason — alongside the ordinary-looking IQ scores below — that the condition is so easy to overlook entirely.

The number that surprises people

Full FAS, the most visibly affected end of the spectrum, carries a reported average full-scale IQ of around 70. The much larger nondysmorphic group, most of ARND, averages closer to 80, solidly in the low-average range and well outside the range most people picture as "intellectually disabled." The 1996 clinical study cited above found that even inside a sample of people who had already received an FAS or related diagnosis, only 16 percent scored low enough on IQ testing to meet criteria for intellectual disability. The obvious implication is the one that matters clinically: an ordinary IQ score is common in FASD, not an exception to it, and cannot be used on its own to rule the condition in or out.

Bar chart of executive-function deficits in fetal alcohol spectrum disorder versus typically developing peers, in standard deviation units: planning 0.94, fluency 0.87, set-shifting 0.87, working memory 0.84, vigilance 0.52, inhibition 0.50 below average, from Kingdon et al. 2016
Your own number

Where would your own score land?

Take the IIF-certified assessment and get your score with the scale it was measured on, the percentile it corresponds to and the confidence range around it — the three figures most online tests leave out.

Find your IQ score now! →

Secure & encryptedInstant results10–20 minutes

The profile underneath an ordinary-looking score

A 2016 meta-analysis in the Journal of Child Psychology and Psychiatry pooled the executive-function research and found a specific, consistent pattern relative to typically developing peers: large deficits in planning (0.94 standard deviations below average), verbal fluency (0.87), set-shifting (0.87) and working memory (0.84), with smaller but still real gaps in sustained attention (0.52) and inhibitory control (0.50). Other work has found working-memory deficits specifically that hold up even after global IQ is statistically controlled for — meaning the memory problem is not simply a byproduct of a lower overall score, but something that shows up on top of it. The same meta-analysis compared FASD directly against ADHD, since the two conditions are frequently confused: fluency and planning deficits were significantly worse in FASD, while vigilance and inhibition were not reliably distinguishable between the two groups, a genuinely useful and specific finding for anyone trying to tell them apart.

A complication worth stating honestly

Not every study finds executive function singled out this cleanly. A large 2021 analysis pooling six prospective U.S. cohorts, adjusted for socioeconomic status and other substance exposure, found alcohol-associated effects of roughly similar size across learning and memory, executive function, reading and math, rather than one domain standing out sharply from the rest — and found no statistically significant effect on sustained attention specifically, where the meta-analysis above did find one. The honest summary is that a specific, disproportionate executive-function signature is well supported by a substantial body of clinical research, but it is not uncontested, and the most recent large multi-cohort analysis complicates a version of the story that treats it as fully settled.

Why the diagnosis gets missed so often

A school-based study cited in a 2019 Lancet Neurology review found that fewer than 1 percent of the children who actually met FASD criteria on structured assessment had ever received a clinical diagnosis. An ordinary-looking composite score, a lack of the facial features most people expect, and a genuine lack of international diagnostic consensus among clinicians themselves all point the same direction: this is a condition that hides in plain sight far more often than it announces itself. Current U.S. prevalence estimates, from active-screening studies in four communities, run from roughly 11 to 50 per 1,000 children by a conservative count and considerably higher, 31 to 98 per 1,000, in a more thorough weighted estimate — CDC’s rounded public figure, "up to 1 in 20," is the upper end of that range, not a single settled number.

None of this is about assigning blame. Research on how this condition gets discussed has moved deliberately away from framing centered on a mother’s choices, in part because messaging that reads as accusatory has not been shown to change drinking behavior and can make people less willing to seek a diagnosis or support once a child is already showing signs. The clinical goal is identifying the actual cognitive profile early enough to help, not assigning responsibility for it after the fact.

What this means for testing and support

The practical lesson runs the same direction as it does for the conditions covered in this site’s companion piece on ADHD, autism and dyslexia: a single composite score was never built to capture a profile this specific, and for FASD in particular, a normal full-scale number is common enough that it should never be treated as evidence against the diagnosis on its own. Formal neuropsychological testing, the kind used in a full child assessment rather than a single screening number, is what actually surfaces the planning, fluency and working-memory pattern described above, and it is that pattern, not the IQ score sitting on top of it, that should drive decisions about accommodations and support.

This is one entry in a small set of ways early life can shape later cognitive outcomes through a mechanism that has nothing to do with inherited ability — see this site’s companion piece on chronic early-life stress for a very different kind of exposure that leaves a recognizably similar signature: an average score that is not the whole story. For the much broader question of how much of any IQ score is inherited in the first place, see is IQ genetic.

Share this article

Know someone who keeps seeing these numbers quoted without the scale they were measured on? Send it to them.

Tagged child iq, cognitive development, diagnosis and assessment, executive function, FASD, fetal alcohol spectrum disorder, intelligence research, IQ Science, iq testing for children, nature versus nurture, neurodevelopmental disorder, prenatal alcohol exposure, Test Accommodations, Working Memory